
Chagas Disease (American trypanosomiasis)
Key points
-
Chagas disease is caused by the parasite Trypanosoma cruzi and transmitted in the feces of infected triatomine bugs, which defecate during or after taking a blood meal.
-
The disease is endemic only in Latin America.
-
Children with acute infection are more likely to be symptomatic than adults.
-
The acute phase may be asymptomatic or include nonspecific symptoms and signs.
-
The chronic phase occurs 10 to 30 years later and may include cardiac or gastrointestinal symptoms.
-
Congenital infection occurs in an estimated 3% to 15% of newborns of infected mothers. Vertical transmission accounts for approximately 30% of all Chagas cases.
-
Screening of blood donors and blood is done to prevent transmission via blood and blood products.
-
Diagnosis in the acute phase is by detecting the parasite in a blood smear and/or by PCR; diagnosis in the chronic phase is by serology, PCR in chronic disease has lower sensitivity.
-
Treatment with benznidazole or nifurtimox is recommended for all cases of congenital, acute and chronic Chagas disease in children and youth younger than 18 years of age. This is to prevent evolution to chronic disease in adulthood with subsequent end organ damage (cardiac and gastrointestinal) at which point treatment is typically futile.
Introduction
Chagas disease (also referred to as American trypanosomiasis) is caused by the parasite Trypanosoma cruzi, commonly transmitted in the feces of infected triatomine bugs. These relatively large blood-sucking insects, sometimes called ‘kissing bugs’ (Figure 1), are found mainly in Central and Latin America and in the southern United States.1 Species of Triatominae differ by geographic region. The bugs defecate during and after taking a blood meal. The bitten person self-inoculates by inadvertently rubbing insect feces containing the parasite into a bite site, mucous membranes in the eyes or mouth or consuming feces, typically in contaminated juices or water. The disease can be transmitted congenitally, from an infected mother to her baby and (less commonly) by blood transfusion, an organ transplant or contaminated food and drink.2 Vertical transmission occurs in an estimated 3% to 15% of newborns of infected mothers.3 Vertical transmission accounts for approximately 30% of all Chagas cases.4
Figure 1. Adult female kissing bug of the species Triatoma rubida. Scale bar = 1 cm.

Photo credit: Reisenman CE, Lawrence G, Guerenstein PG, et al. Infection of Kissing Bugs with Trypanosoma cruzi, Tucson, Arizona, USA. Emerg Infect Dis 2010;16(3). Photograph by C. Hedgcock
Epidemiology
The WHO estimates that approximately 8 million people worldwide are infected with T. cruzi accounting for 10,000 deaths/year. More than 100 million people are considered at risk of infection. An estimated 10,000 congenitally-acquired cases occur annually. Whereas Chagas was previously predominantly isolated to rural areas of Latin America, most infected people now live in urban areas.5 Data on the prevalence of Chagas disease in newcomers to Canada are limited, particularly in young newcomers. One study estimated that 3.5% of immigrants to Canada from Latin America were infected with the disease in 2006 though in surveillance date few cases of disease are reported in Canada.2,6
Risk factors
Endemic areas include Mexico, Central America and South America.5 While parts of the southern U.S. have enzootic cycles of T. cruzi involving triatomine bugs and mammals, notably racoons, opossums and dogs, most Chagas cases occur in immigrants from other countries.5,7
Severity of infection
Initial infection may be asymptomatic. The disease has 2 phases of differing severity 2,5,8:
- First (acute) phase: Occurs soon after infection, with mild nonspecific symptoms (see Table 1) that resolve over 2 to 3 months without treatment. Rarely, the illness is severe, causing myocarditis and/or meningoencephalitis, which can be fatal. Severe symptoms occur more often in children, the elderly and the immunocompromised.
- Second (chronic) phase: Most patients with chronic T. cruzi infection have no symptoms. This asymptomatic chronic phase is known as the ‘indeterminate’ form. However, in 20% to 30% of cases, serious progression occurs 10 to 30 years after the initial infection. In the symptomatic chronic phase, cardiac manifestations may occur, including Chagas myocardopathy with conduction system abnormalities, right bundle branch block, complete heart block or ventricular arrhythmias, or congestive heart failure. Gastrointestinal manifestations include megaesophagus, megacolon and weight loss.
Clinical clues
The first (acute) and second (chronic) phases of Chagas disease are associated with different symptoms, summarized in Table 1.
|
First phase: Acute symptoms |
Second phase: Chronic symptoms |
|---|---|
| May occur one or more weeks after infection and last 2 to 3 months | May occur 10 to 30 years after initial infection |
|
|
|
* Romaña's sign is a result of conjunctival contamination with triatomine feces. Source: Adapted from Government of Canada (Travel.gc.ca) Travelling Abroad, Travel Health and Safety, Diseases, American trypanosomiasis (Chagas disease). |
|
Diagnosis
A diagnosis of Chagas disease is based on laboratory testing following consideration of a patient’s clinical findings and infection risk. In Canada, the National Reference Centre for Parasitology (NRCP) in Montreal is the resource to contact about Chagas testing. If a patient tests positive, household members should also be tested if they have had similar exposures to triatomine bugs.
Testing formats depend on the phase of suspected disease9:
First (acute) phase
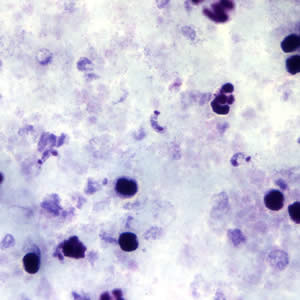
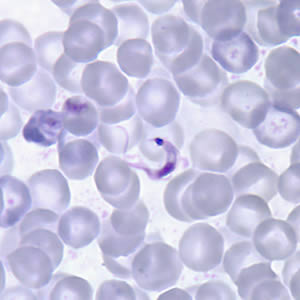
Identify circulating parasites (trypomastigotes) in a blood smear by microscopy (Figure 2). With central nervous system infections, trypomastigotes may be seen in cerebrospinal fluid.
Figure 2: T. cruzi trypomastigotes in a blood smear
Thick Smear
Thin Smear
Source: Centers for Disease Control and Prevention. Public Health Image Library: https://www.cdc.gov/dpdx/trypanosomiasisamerican/index.html.
Second (chronic) phase
Use two or more serological tests for antibody to the parasite (i.e., enzyme-linked immunosorbent assay [ELISA] and immunofluorescent antibody test [IFA]). Circulating parasite levels are generally undetectable during the chronic phase of infection.
Screening
At-risk pregnant women, their newborns, and older children
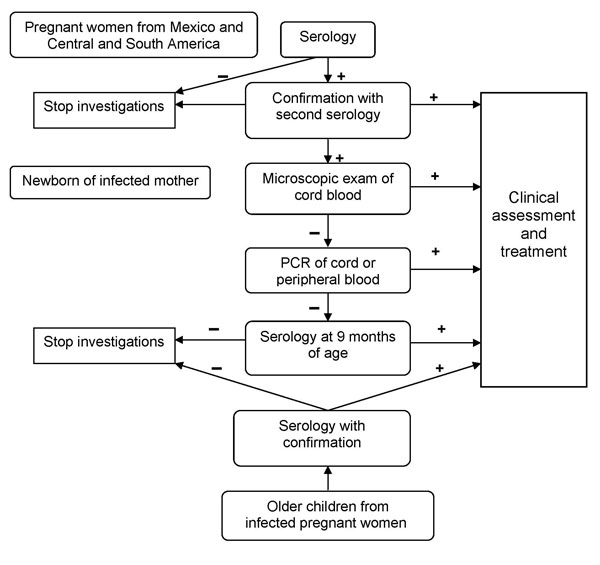
All children with epidemiologic risk or born to mothers with epidemiologic risk or with confirmed T. cruzi infection should be tested for Chagas disease (Figure 3).
Figure 3: Algorithm suggested by Geneva University Hospitals, Switzerland, for Pregnant Women from Latin America
Source: Jackson Y, Myers C, Diana A, et al. Congenital transmission of Chagas disease in Latin American immigrants in Switzerland. Emerg Infect Dis 2009;15(4):601-3. With permission.
Blood donors and blood
Canadian Blood Services screens those blood samples from donors with epidemiologic risks.
Treatment
Treatment for Chagas disease is recommended for all cases of congenital acute and chronic disease in children and adolescents younger than 18 years of age.8 The only antimicrobials proven to work are benznidazole and nifurtimox. Both drugs require special access through Health Canada. The disease can be cured if treatment is initiated soon after infection; however, the efficacy of treatment diminishes with increasing length of infection. Symptomatic treatment may also be required.
Prevention
There is no vaccine against Chagas disease. Preventing triatomine bug bites is the best protection against Chagas disease when travelling or living in endemic regions:
-
Do not camp or sleep outside,
-
Avoid mud, palm thatch or adobe brick structures, which are vulnerable to infestation,
-
Use insecticide-impregnated bed nets, and
-
Examine living quarters for signs of infestation and exterminate if found.
More information on preventing insect bites can be found in the Travel-Related Illness page of this resource.
Breastfeeding
Although data is limited, mothers with Chagas disease can continue to breastfeed unless they are in the acute phase of the disease, have reactivated disease due to immunosuppression, or have bleeding nipples.10
Selected resources
-
Centers for Disease Control and Prevention. Parasites - American Trypanosomiasis (also known as Chagas Disease)
-
Government of Canada. American Trypanosomiasis (Chagas disease)
References
- Reisenman CE, Lawrence G, Guerenstein PG, et al. Infection of Kissing Bugs with Trypanosoma cruzi, Tucson, Arizona, USA. Emerg Infect Dis 2010;16(3).
- Government of Canada. American Trypanosomiasis (Chagas disease).
- Klein MD, Proaño A, Noazin S, Sciaudone M, Gilman RH, Bowman NM. Risk factors for vertical transmission of Chagas disease: A systematic review and meta-analysis. Int J Infect Dis. 2021 Apr;105:357-373.
- Howard EJ, Xiong X, Carlier Y, Sosa-Estani S, Buekens P. Frequency of the congenital transmission of Trypanosoma cruzi: a systematic review and meta-analysis. BJOG An Int J Obstet Gynaecol 2014;121:22–33.
- World Health Organization. Chagas disease (also known as American trypanosomiasis). Fact sheet N°340. Geneva, Switzerland: WHO, updated April 2026.
- Schmunis GA, Yadon ZE. Chagas disease: A Latin American health problem becoming a world health problem. Acta Trop 2010;115(1-2):14-21.
- Bern C, Kjos S, Yabsley MJ, Montgomery SP. Trypanosoma cruzi and Chagas' Disease in the United States. Clin Microbiol Rev. 2011 Oct;24(4):655-81.
- American Academy of Pediatrics. American Trypanosomiasis (Chagas disease). In: Kimberlin DW, Banerjee R, Barnett ED, et al., eds. Red Book: 2024–2027 Report of the Committee on Infectious Diseases. 33rd ed. American Academy of Pediatrics; 2024.
- Centres for Disease Control and Prevention. Chagas Disease. Diagnosis. September 2024.
- Norman FF, López-Vélez R. Chagas disease and breast-feeding. Emerg Infect Dis 2013;19(10):1561-6.
Reviewer(s)
Justin Penner, MD
Last updated: August, 2026